
With the national campaign to vaccinate all human life in the UK against Covid-19 in full swing, and with no properly approved Covid-19 vaccine in sight until around 2023 when the first vaccine manufacturer’s trials are due to be completed, we might pause to ask ourselves some pertinent questions:
- In view of the critical importance of safety in these vaccination programmes, why are these vaccine trials being run by the manufacturers who have an overwhelming financial and (arguably) reputational interest in obtaining a positive outcome?
- Why were the manufacturers given an absolute indemnity from prosecution for damage caused by their vaccines?
- On what evidential basis did the MHRA give emergency approval for the vaccine roll-out?
- Given that six months have elapsed since commencing the roll-out, what steps has the MHRA taken to investigate the Yellow Card reports of vaccine adverse events, in order to learn from experience in the field and to adopt appropriate measures to limit and mitigate such events in the future?
- Why has the MHRA maintained radio silence on the results both from its investigations of the Yellow Card reports, and from any other investigations which it has conducted?
- What evidential criteria did the MHRA consider when deciding that the risks to young people of death and injury from taking the vaccine(s) would be less than the risk of death and injury from catching Covid-19?
- Have any of these questions been pursued in Parliament? If so, with what result?
- Why does our Government consider that any of these matters are satisfactory from the point of view of anyone without connections to the pharmaceutical industry?
With the above unanswered questions in mind and in the absence of any discernible intention to provide answers, it’s time to look elsewhere.
This article in Left Foot Forward by Professor Prem Sikka provides a pertinent summary of governmental failure to tackle what many perceive as corruption in high places. It sets a backcloth to the more specific debate about how the government has been handling the Covid crisis (explored in more depth by the Good Law Project).
This article by the Bernician explores the role of the JCVI (Joint Committee on Vaccination and Immunisation) and some legal constraints that may compel the Secretary of State for Health and Social Care to implement their advice. It covers their role in supporting all the usual childhood vaccinations.
On 4th June 2021 the MHRA concluded a positive safety profile for Pfizer/BioNTech vaccine in 12-to-15-year-olds:
“Over 2000 children aged 12-15 years were studied as part of the randomised, placebo-controlled clinical trials. There were no cases of COVID-19 from 7 days after the second dose in the vaccinated group, compared with 16 cases in the placebo group. In addition, data on neutralising antibodies showed the vaccine working at the same level as seen in adults aged 16-25 years. These are extremely positive results”.
Well, let’s see – since 2000 children in this age group were split into two groups (placebo and vaccine) then we may reasonably assume that only 1000 children of this age group in the entire trial were given the vaccine. Lets us further assume that there were zero severe adverse reactions / deaths (however defined) in this group.
Some elementary statistics show that:
- If the underlying incidence of adverse events per 1000 is 4.5, then the chance that this trial would return no events is close to 1%
- If the underlying incidence of adverse events per 1000 is 1, then the chance that this trial would return no events is close to 36%
- If the underlying incidence of adverse events per 1000 is 0.5, then the chance that this trial would return no events is close to 60% (assuming a Poisson distribution of the random occurrence of rare events in a given time-frame – or in this case per 1000 vaccinations, which is a sufficient approximation given how little detail we know)
So from this data we may deduce with very high confidence that the underlying rate of adverse events per 1000 lies in the range 0 to 5, with expected value somewhere around 0.7 per 1000.
Statistically speaking, this trial per se cannot be relied upon to determine that vaccinating the entire population of children in this age group is ‘safe’ in a way that would be understood by any reasonable parent, whilst the chance of their offspring suffering an equivalent event from falling ill with the disease is estimated to be at least an order of magnitude below 1 in 1000.
The trial simply did not have a sufficient number of participants to demonstrate safety as compared with not vaccinating.
For comparison we show below the Public Health England week 24 hospital Covid-19 admissions graph by age group:
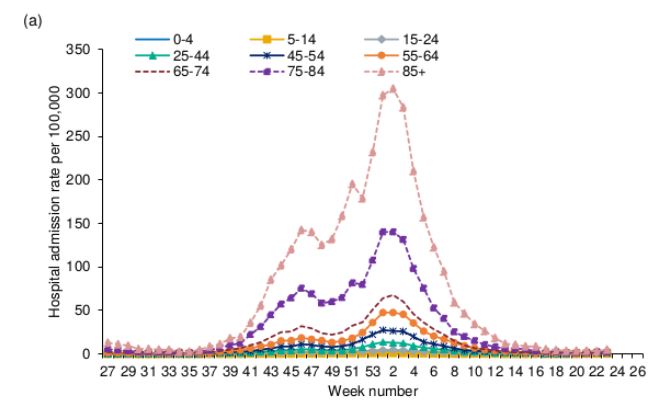
Can you find the lines for 5-14 and 15-24 years old?
Still want validation? This article in the Telegraph sums it up. It’s behind a paywall, but the title says it all.
If matters are so dire, where are the whistle-blowers? Well, here actually, as reported by Conservative Woman. And you can download the whistle-blower’s comprehensive legal response to Sir Simon Stevens here.
I suggest keeping it handy as a compendium of all matters Covid-19 inoculation for future reference.



Now we can compare outcomes in different territories it is clear Lockdowns and Masks make little difference to infection and the harsher the regime the greater the collateral damage – In other words it has all been pointless from an infection perspective and a catastrophe from all other perspectives – Lets hope this experimental injection of entire nations works out better – The side effects like menstrual disturbance does not look encouraging and the proposal of auto immune consequences further down the pipe are of concern – But hey it’s an experiment and you have got to expect some tweaking to be required before the next experiment until you get it right, well surely that is the whole point of experimenting.
Excellent article thanks. Let’s face it, like any politician B.J. has to grab any available feather to pin in his hat. The vaccine roll out provided one.
As to ‘the expert’ comment. Presumably that commenter is impressed by all the models that have been produced over the years by the expert known as Professor Ferguson.
Apologies. It was a non-expert comment. You know who I mean.
If they posted the information contained, both in the article and some of the comments to it, outside COVID ‘snake oil’ jabbing centres I wonder how many people would cancel their appointments???
Thank you to Jim and also to the commenters who have posted highly interesting and illuminating information for the rest of us to assimilate. Having read it all, the prime emotions filling my soul are monumental anger and disgust at the traitorous actions of those who have clawed their way up the greasy pole of ambition and avarice to the detriment of us all!
Thank you for an interesting and necessary article Jim but we need a large proportion of the populace at large to open their minds and reject the government propaganda. There is much evil intent in the world; Boris would have been wise to reject the ideas of the G7 members and put our country and its people first. Some hope.
You wonder if so many people would have wanted the untrialled vaccines against Covid-19, if they knew that the Human Medicines Regulations were altered in October 2020, so that producers of untrialled Covid vaccines cannot be sued.
Did those people know that untrialled Covid vaccines could only be authorised for emergency use in the absence of any adequate, approved, and available alternatives? (Which makes it utterly obvious that the suppression of Hydroxychloroquine with Zinc Sulphate as an alternative cure for Covid is proof of corruption in high places).
Did those people know that authorisation for emergency use of untrialled vaccines can only be given in a “public health emergency”? If so, then those people might have treated the endless Project Fear Covid from our mainstream media with more scepticism. The BBC is clearly determined to convince us all that Covid-19, the 21st century’s Black Death, is a “public health emergency”, and that only untrialled vaccines can save us all.
Did those people know that even though Influenza and Pneumonia are “mentioned” more often on death certificates, the Office of National Statistics (ONS) has decided that Covid-19 was “the underlying cause of death” in “over three times” as many cases as them? That ONS press release didn’t say that Flu & Pneumonia were “mentioned” as the cause of death more often on those death certificates. Nor that “over three times” could actually be over twenty times, if the ONS feels like it.
I see the non-experts are out again!
This below By
Maxwell
most upticks BTL
https://off-guardian.org/2021/07/03/whistle-blowing-doctors-open-letter-to-the-head-of-the-nhs/
Jul 4, 2021 1:39 AM
Some data from the UK.
– Comparing the death rate of 2020 with previous 20 years.
2020 rate was 1,037/100,000 in the UK. Highest in 10 years but not the highest in the last 20 years.
What happened?
2008 had a death rate of 1,084/100,000.
2005 had 1,137/100,000.
Every year prior to 2009 had a higher death rate than 2020.
– UK Lockdown was towards end of March in 2020;
– At home deaths began to escalate in April.
5 year avg. for deaths in April previous to 2020 was 9,384. In April 2020 there were 16,909 at home deaths;
5 year average for deaths in care homes in April was 8,691. In April 2020 there were 26,541 deaths that occurred in care homes. An astronomical increase.
Hospital data for April 2017- 2020:
April-June 2017– 91,724 beds occupied= 89% occupancy rate;
April-June 2018– 91,056 beds occupied= 90% occupancy rate;
April-June 2019– 91,730 beds occupied= 90% occupancy rate;
April-June 2020 58,005 beds occupied= 62% occupancy rate.
2018 – April – 1,984,369 attended A&E (Accident and Emergency)
2019 – April – 2,112,165 attended A&E
2020 – April – 916,581 attended A&E
Important Notes:
30% less hospital beds occupied in April – June 2020 compared with previous 3 years.
A&E in April 2020 was 57% down from 2019.
These numbers explain the high numbers of at home deaths.
Increase in deaths occurring at home and in care homes in April 2020 due to not being treated for illnesses in hospital. No acute care in private homes or care homes.
CAUSE OF DEATHS USING DECEMBER 2020 AS EXAMPLE:
– Leading cause of death was stated as “Covid-19 deaths”- 10,973 deaths for December 2020.
– 2nd leading cause of death in December 2020- Dementia and Alzheimer’s- 5281 deaths.
Previous 5 year average for December- 28,198 deaths due to Dementia and Alzheimer’s.
This is a 500%+ alteration from previous 5 years. A statistical impossibility.
– Heart disease deaths in December 2020- 4,635 deaths.
December 5 year average- 21,997 deaths.
This represents a near 500% statistical deviation from previous 5 year average- also not possible.
– Chronic lower respiratory disease deaths December 2020- 1,790 deaths.
December 5 year average- 13,384 deaths.
This represents about a 700% detour from the 5 year average. Not possible.
– Influenza and pneumonia deaths in December 2020- 1,190 deaths.
December 5 year average- 11,295 deaths.
This represents about a 1000% deviation from the 5 year average.
What is left to say?
It seems it would take quite a monumental argument to prove that the death certificates have not been manipulated. It would take an even grander argument to illustrate that the NHS was under pressure at any time as during the height of the “pandemic” at home deaths soared to record heights and hospital and emergency services sunk to all-time lows.
How is this not criminal fraud that resulted in numerous premature and unnecessary deaths?
Excellent post thank you.
Thanks for an excellent article
Many thanks for an excellent article